



Daratumumab, an Anti-CD38 monoclonal antibody, is now widely used in frontline induction for transplant-eligible multiple myeloma. Although highly effective, concerns remain regarding its potential impact on CD34⁺ stem cell mobilization and early outcomes after autologous hematopoietic stem cell transplantation, particularly when combined with lenalidomide. This study aims to evaluate whether prior daratumumab exposure affects CD34⁺ mobilization, stem cell collection, engraftment, or early post-autologous hematopoietic stem cell transplantation complications.
Methodsa retrospective, single-center cohort study was conducted in 100 adults who underwent autologous hematopoietic stem cell transplantation. Data on mobilization, CD34⁺ counts, plerixafor use, collection yield, engraftment, infectious complications, engraftment syndrome, intensive care unit admission, and hospitalization were extracted from medical records.
ResultsOf the 100 patients, 46% had received daratumumab therapy. Baseline characteristics were similar except for more frequent prior lenalidomide use in controls (78% versus 35%; p < 0.001). No mobilization failures occurred. Peripheral CD34⁺ levels during mobilization (15 versus 19 cells/µL; p = 0.220) were comparable. Plerixafor use (26% versus 24%; p = 1.0), final CD34⁺ yield (3.80 versus 4.07×10⁶ cells/kg; p = 0.358), and time to neutrophil engraftment (10 versus 10.5 days; p = 0.539) were statistically equivalent. Rates of engraftment syndrome (25%), febrile neutropenia (89%), bacteremia (23%), intensive care unit admission (12%), and hospitalization metrics did not differ significantly. One death occurred in the control group.
ConclusionIn this real-world cohort, no significant differences in CD34⁺ mobilization, apheresis outcomes, engraftment, or early post-autologous hematopoietic stem cell transplantation complications were observed based on prior daratumumab exposure. These findings support the safety and feasibility of autologous hematopoietic stem cell transplantation following anti-CD38-based induction regimens, including those incorporating lenalidomide.
The therapeutic landscape of multiple myeloma (MM) has markedly evolved with the incorporation of anti-CD38 monoclonal antibodies, such as daratumumab, into frontline induction regimens [1]. CD38 is highly expressed on malignant plasma cells, and its targeting promotes direct cytotoxicity, antibody-dependent cellular cytotoxicity, complement activation, and immunomodulatory reshaping of the marrow microenvironment [1,2]. Quadruplet induction regimens combining an anti-CD38 agent with a proteasome inhibitor and an immunomodulatory drug, such as Dara-VRd or Dara-VTd, achieve deeper responses and higher measurable residual disease-negativity rates compared with triplet regimens, establishing anti-CD38 therapy as an increasingly preferred component of first-line treatment for transplant-eligible patients [3–5].
Autologous hematopoietic stem cell transplantation (auto-HSCT) is a cornerstone of the management of patients with multiple myeloma and is associated with prolonged progression-free survival compared to other approaches [1,6]. Therefore, successful mobilization and adequate collection of CD34⁺ hematopoietic stem cells remain essential, even in the era of highly active quadruplet therapy. As induction regimens intensify and exposure to novel agents increases, concerns have emerged regarding their potential effects on stem cell reserve, mobilization kinetics, and subsequent transplant-related complications.
The combination of anti-CD38 monoclonal antibodies with lenalidomide, now widely adopted in quadruplet regimens, has prompted specific concerns about impaired stem cell mobilization. Both lenalidomide and daratumumab have been implicated in reduced CD34⁺ yields, increased plerixafor use, and delayed hematopoietic recovery in some series [7,8]. In contrast, daratumumab-thalidomide–based regimens, such as those examined in the CASSIOPEIA trial, did not demonstrate meaningful impairment in mobilization or collection [3,5]. Biologically, a plausible mechanism exists: CD38 is also expressed on subsets of hematopoietic progenitors, regulatory T cells, and myeloid cells, and its depletion may influence marrow-niche interactions, cytokine profiles, and inflammatory pathways involved in engraftment and immune reconstitution [4]. Nevertheless, clinical findings remain heterogeneous, with several reports showing no significant difference in mobilization success, engraftment, or post-auto-HSCT complications among patients pre-treated with anti-CD38 therapy [9,10].
Given the expanding use of anti-CD38-based induction and the mixed evidence regarding its impact on stem cell collection and transplant outcomes, a single-center real-world study was conducted to evaluate whether prior exposure to daratumumab affects CD34⁺ mobilization, collection yield, engraftment kinetics, or early post-transplant complications in multiple myeloma patients undergoing auto-HSCT.
MethodsStudy design and settingThis retrospective, single-center observational cohort study was conducted at a tertiary hospital (Complexo Hospitalar de Niterói) with established autologous and allogeneic hematopoietic stem cell transplant (HSCT) programs since 2007 and 2013, respectively. The study included consecutive adult patients with multiple myeloma who underwent auto-HSCT between January 2023 and July 2025. This study is part of a prospective cohort of stem cell transplant recipients who have been followed since 2013.
Ethical approvalThe study protocol was reviewed and approved by an institutional regulatory board/ethics committee (CEP Hospital Nove de Julho: approval number: CAAE 54941216.0.3001.5455). All procedures were conducted in accordance with national regulations for research involving human subjects and in accordance with the principles of the Declaration of Helsinki. Because the study was retrospective and used anonymized data, the requirement for informed consent was waived.
ParticipantsEligible participants were adult patients (≥18 years) undergoing auto-HSCT for multiple myeloma during the study period. Two patients were excluded due to incomplete information on pre-transplant therapy, leaving a final cohort of 100 patients. Patients were categorized into two groups according to their exposure to anti-CD38 monoclonal antibodies prior to transplant: the Anti-CD38-exposed group and the Control (Non–anti-CD38 control) group.
Peripheral blood (PB) CD34+ cell counts were assessed, by routine, on Day 4 of granulocyte colony-stimulating factor (G-CSF) mobilization. Patients with PB CD34+ counts >10 cells/µL proceeded directly to apheresis, whereas patients with counts <10 cells/µL received plerixafor, with apheresis initiated on Day 5, as part of the institutional preemptive plerixafor strategy.
Data collectionData were extracted from electronic medical records and transplant program databases by trained investigators using a standardized data collection form. Variables collected included demographic characteristics, disease status at auto-HSCT, prior therapies, mobilization regimen, CD34⁺ counts in PB at Day 4 of mobilization, plerixafor use, CD34⁺ yield, infusion method (fresh vs. cryopreserved), engraftment outcomes, infectious complications, intensive care unit (ICU) admission, and hospitalization duration. Data were checked for completeness and accuracy by a second reviewer.
Definitions- •
Mobilization failure: Inability to proceed to apheresis due to insufficient CD34⁺ mobilization; no such failures occurred in this cohort.
- •
PB CD34⁺ count: CD34⁺ quantification at Day 4 of stem cell mobilization.
- •
Successful collection: Collection of ≥2 × 10⁶ CD34⁺ cells/kg, per institutional standards.
- •
Engraftment: First of three consecutive days with absolute neutrophil count ≥500/µL.
- •
Engraftment syndrome (ES): Defined according to the Maiolino criteria [11].
- •
Febrile neutropenia: Fever ≥38.3 °C once or ≥38.0 °C sustained for ≥1 hour with absolute neutrophil count <500/µL.
- •
Bacteremia: Any positive blood culture or documented clinical infection compatible with bloodstream infection.
- •
Microbiologically documented episodes (without bacteremia): microbiologically confirmed infections from non-bloodstream sites.
- •
Time to engraftment and hospitalization metrics: Counted from Day 0 (stem cell infusion).
The outcomes were the impact of prior anti-CD38 exposure on CD34⁺ mobilization (assessed by PB CD34⁺ counts), need for plerixafor, and CD34⁺ collection yield, engraftment kinetics, ES, febrile neutropenia, bacteremia, ICU admission, duration of hospitalization and early mortality until Day +30.
Statistical analysisStatistical analyses were performed using SPSS software (IBM SPSS Statistics, version 27). Continuous variables were summarized as medians with ranges and compared using the Mann-Whitney U test. Categorical variables were presented as frequencies and percentages and compared using the Chi-square or Fisher’s exact test where appropriate. All tests were two-sided, and p-values <0.05 were considered statistically significant. Missing data were reported explicitly and were not imputed. No sample size calculation was performed due to the retrospective nature of the study. Effect sizes were estimated using Cohen’s d based on observed mean differences and pooled standard deviations.
ResultsBetween January 2023 and the first semester of 2025, a total of 103 auto-HSCT were performed for multiple myeloma. Two procedures were excluded due to missing pre-transplant treatment data, leaving 101 eligible patients for analysis. Overall, 47 patients (47%) had received anti-CD38 monoclonal antibodies before auto-HSCT: in one case the drug was isatuximab, but all others received daratumumab. To avoid overgeneralization of anti-CD38 agents, and improve the accuracy of the analysis, the single isatuximab-exposed patient was excluded (n = 100).
The most frequent induction combinations were Dara-VTd (daratumumab, bortezomib, thalidomide, and dexamethasone) and Dara-VRd (daratumumab, bortezomib, lenalidomide, and dexamethasone) in 28 (60%) and 13 (28%) cases, respectively. The most frequent frontline induction regimens without anti-CD38 were VRd (bortezomib, lenalidomide, and dexamethasone: n = 42; 78%), followed by VCd (bortezomib, cyclophosphamide, and dexamethasone: n = 6; 11%). Other combinations were uncommon.
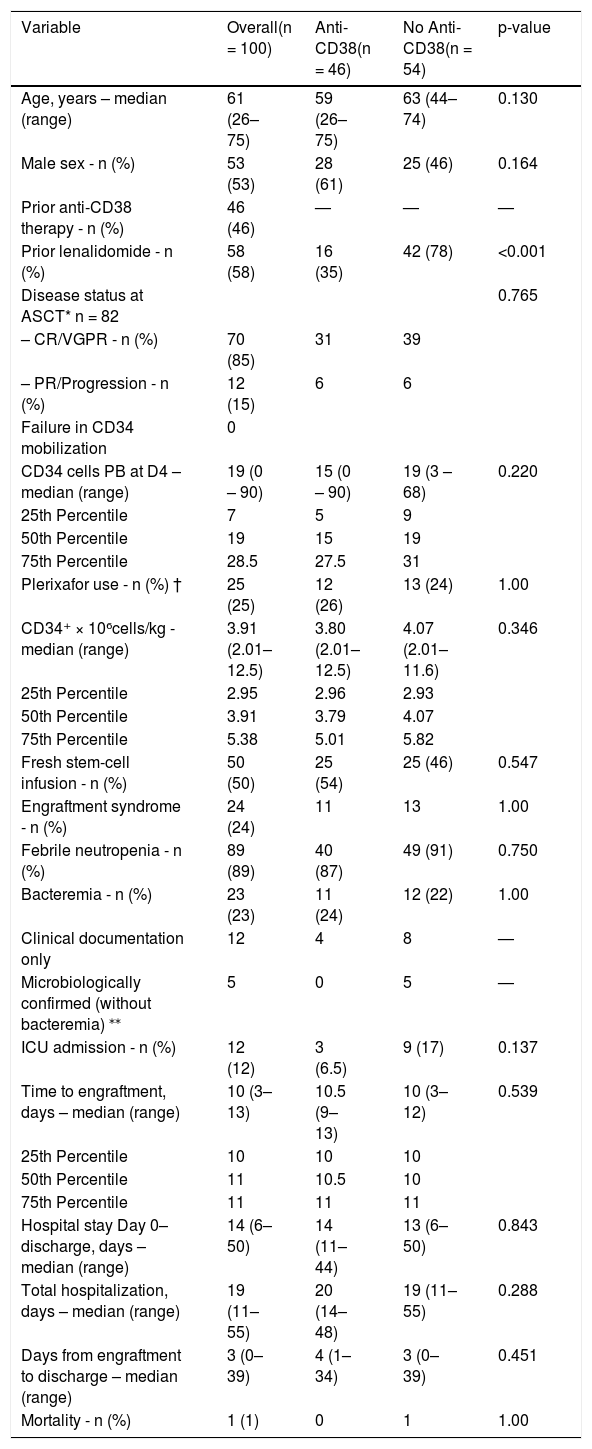
The median age of the cohort was 61 years (range: 26–75), with no significant difference between patients previously exposed to anti-CD38 therapy and those who were not (59 vs. 63 years; p = 0.13). Males accounted for 53% of the population, with no difference between groups (61%vs. 46%; p = 0.164). Prior lenalidomide exposure was significantly more common in the control group (78%vs. 35%; p < 0.001) (Table 1).
Baseline characteristics, mobilization outcomes, and transplant-related complications according to prior Anti-CD38 exposure (n = 100).
| Variable | Overall(n = 100) | Anti-CD38(n = 46) | No Anti-CD38(n = 54) | p-value |
|---|---|---|---|---|
| Age, years – median (range) | 61 (26–75) | 59 (26–75) | 63 (44–74) | 0.130 |
| Male sex - n (%) | 53 (53) | 28 (61) | 25 (46) | 0.164 |
| Prior anti-CD38 therapy - n (%) | 46 (46) | — | — | — |
| Prior lenalidomide - n (%) | 58 (58) | 16 (35) | 42 (78) | <0.001 |
| Disease status at ASCT* n = 82 | 0.765 | |||
| – CR/VGPR - n (%) | 70 (85) | 31 | 39 | |
| – PR/Progression - n (%) | 12 (15) | 6 | 6 | |
| Failure in CD34 mobilization | 0 | |||
| CD34 cells PB at D4 – median (range) | 19 (0 – 90) | 15 (0 – 90) | 19 (3 – 68) | 0.220 |
| 25th Percentile | 7 | 5 | 9 | |
| 50th Percentile | 19 | 15 | 19 | |
| 75th Percentile | 28.5 | 27.5 | 31 | |
| Plerixafor use - n (%) † | 25 (25) | 12 (26) | 13 (24) | 1.00 |
| CD34⁺ × 10⁶cells/kg - median (range) | 3.91 (2.01–12.5) | 3.80 (2.01–12.5) | 4.07 (2.01–11.6) | 0.346 |
| 25th Percentile | 2.95 | 2.96 | 2.93 | |
| 50th Percentile | 3.91 | 3.79 | 4.07 | |
| 75th Percentile | 5.38 | 5.01 | 5.82 | |
| Fresh stem-cell infusion - n (%) | 50 (50) | 25 (54) | 25 (46) | 0.547 |
| Engraftment syndrome - n (%) | 24 (24) | 11 | 13 | 1.00 |
| Febrile neutropenia - n (%) | 89 (89) | 40 (87) | 49 (91) | 0.750 |
| Bacteremia - n (%) | 23 (23) | 11 (24) | 12 (22) | 1.00 |
| Clinical documentation only | 12 | 4 | 8 | — |
| Microbiologically confirmed (without bacteremia) ⁎⁎ | 5 | 0 | 5 | — |
| ICU admission - n (%) | 12 (12) | 3 (6.5) | 9 (17) | 0.137 |
| Time to engraftment, days – median (range) | 10 (3–13) | 10.5 (9–13) | 10 (3–12) | 0.539 |
| 25th Percentile | 10 | 10 | 10 | |
| 50th Percentile | 11 | 10.5 | 10 | |
| 75th Percentile | 11 | 11 | 11 | |
| Hospital stay Day 0–discharge, days – median (range) | 14 (6–50) | 14 (11–44) | 13 (6–50) | 0.843 |
| Total hospitalization, days – median (range) | 19 (11–55) | 20 (14–48) | 19 (11–55) | 0.288 |
| Days from engraftment to discharge – median (range) | 3 (0–39) | 4 (1–34) | 3 (0–39) | 0.451 |
| Mortality - n (%) | 1 (1) | 0 | 1 | 1.00 |
CR: complete response; VGPR: very good partial response; PR: partial response; PB: Peripheral blood; ICU: Intensive care unit.
Among the 82 patients with available staging data, 85% were in complete response/very good partial response at the time of transplantation, with identical distribution across anti-CD38–exposed and control groups (86%vs. 86%; p = 0.765). The interval between diagnosis and auto-HSCT could not be compared due to incomplete data.
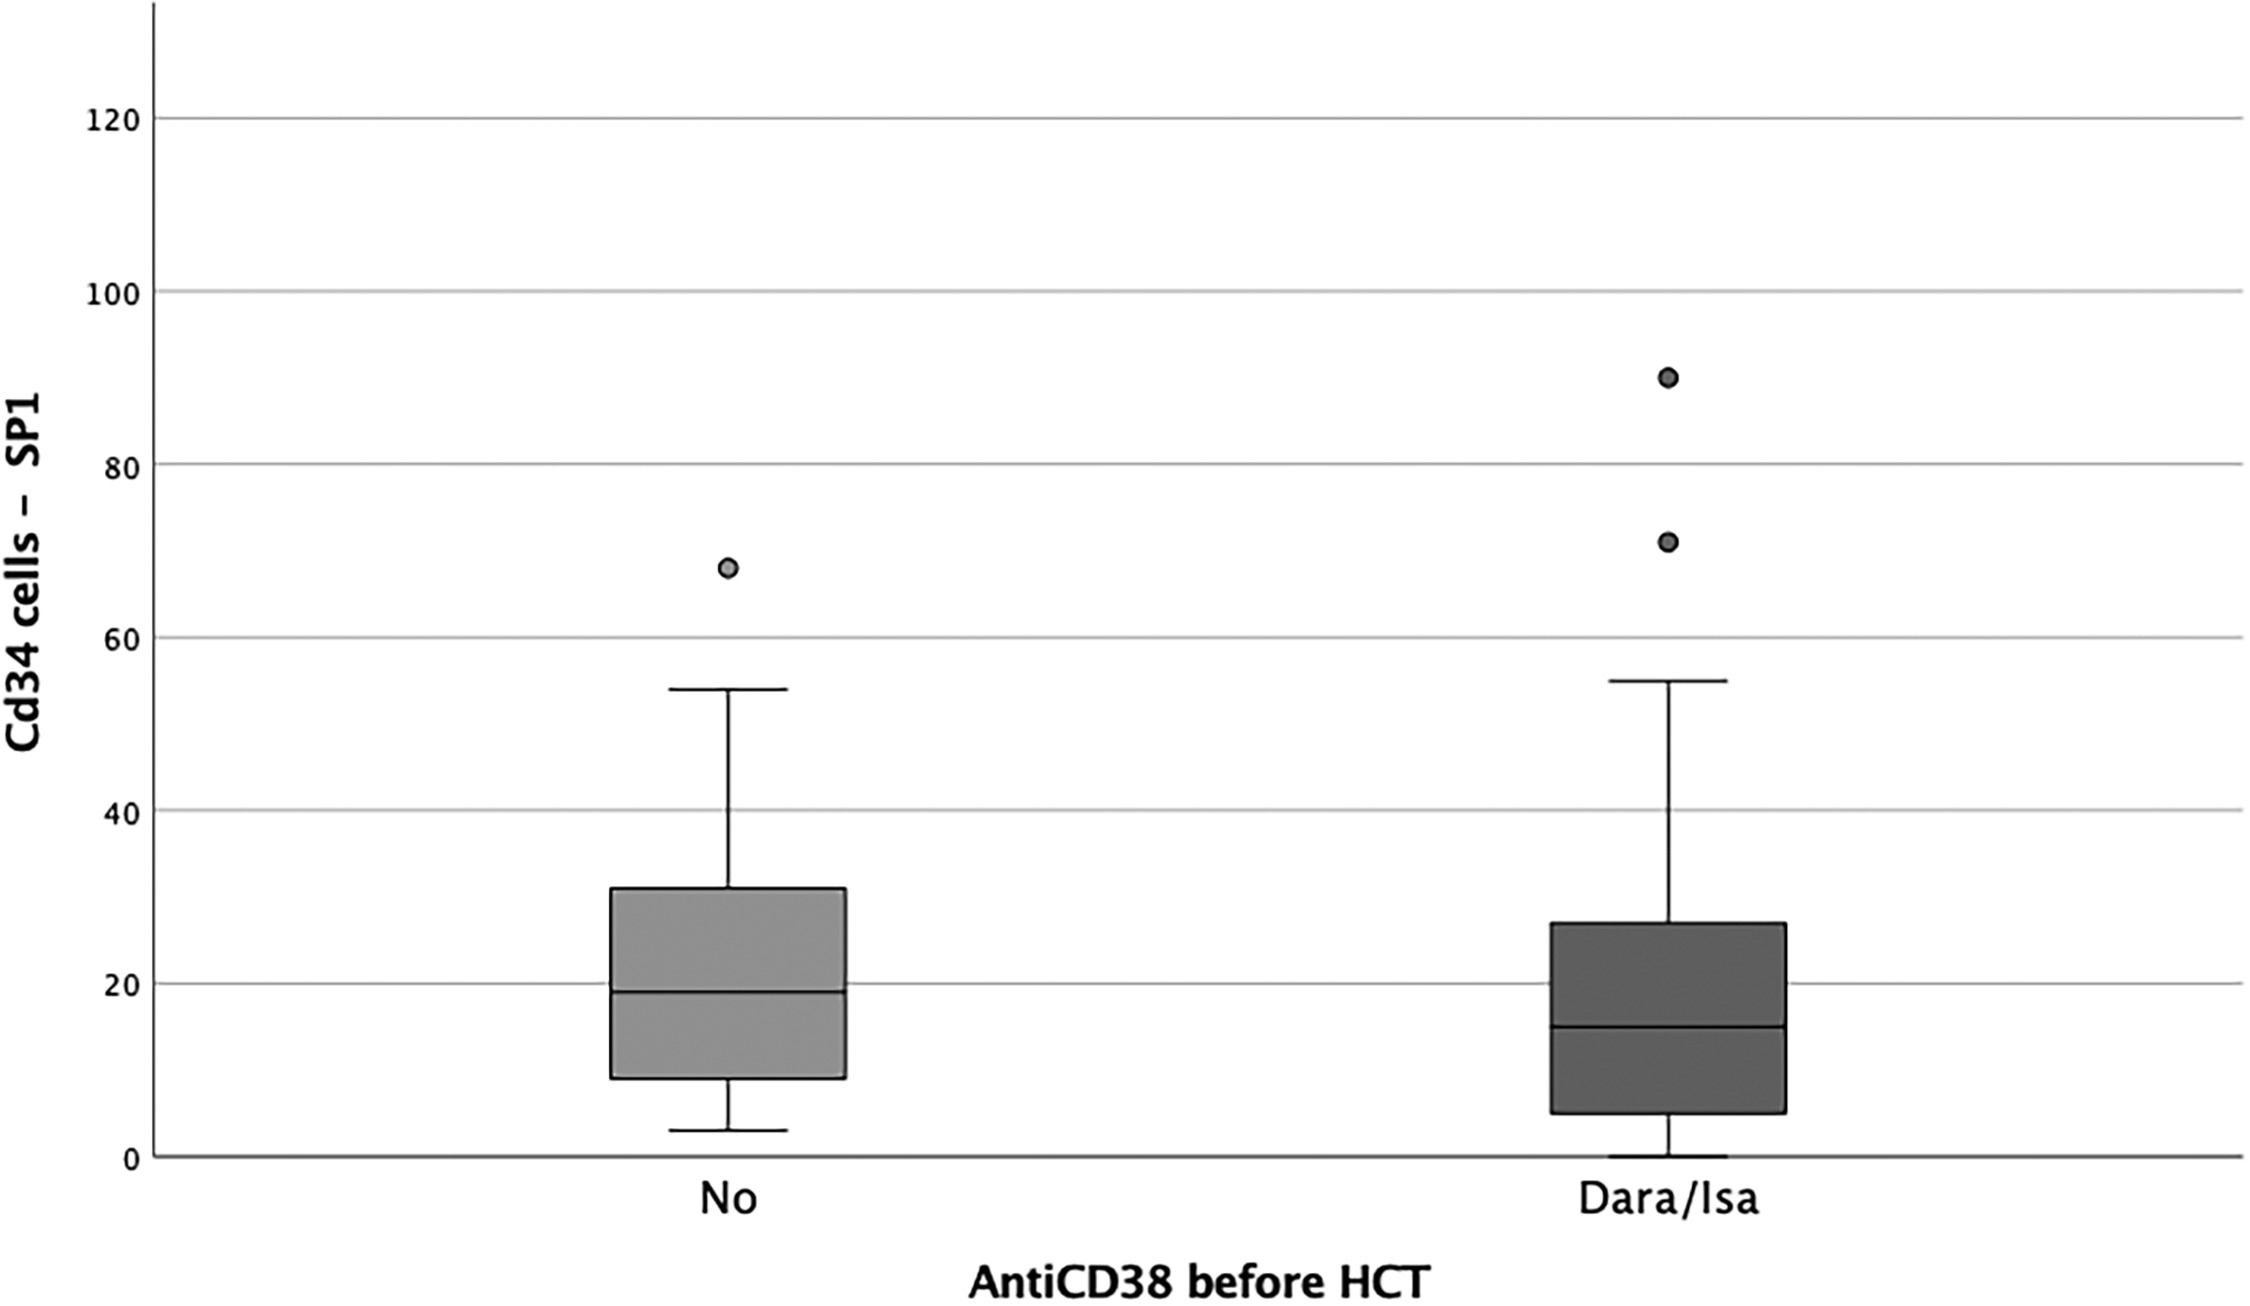
Mobilization, collection, and engraftmentMobilization outcomes were similar between the groups. No cases of mobilization failure were observed in either cohort, and all received G-CSF with or without plerixafor. No patient received chemotherapy regimens for mobilization. Day 4 CD34⁺ quantification in PB showed no significant differences (median 15 vs. 19 cells/µL; p = 0.220) (Figure 1).

Use of plerixafor was comparable (12 vs. 13 patients; p = 1.0), and the final CD34⁺ stem cell yield did not differ between groups (median 3.80 vs. 4.07 × 10⁶/kg; p = 0.346). Half of the cohort received a fresh stem cell infusion, with no difference in anti-CD38 exposure (p = 0.547).
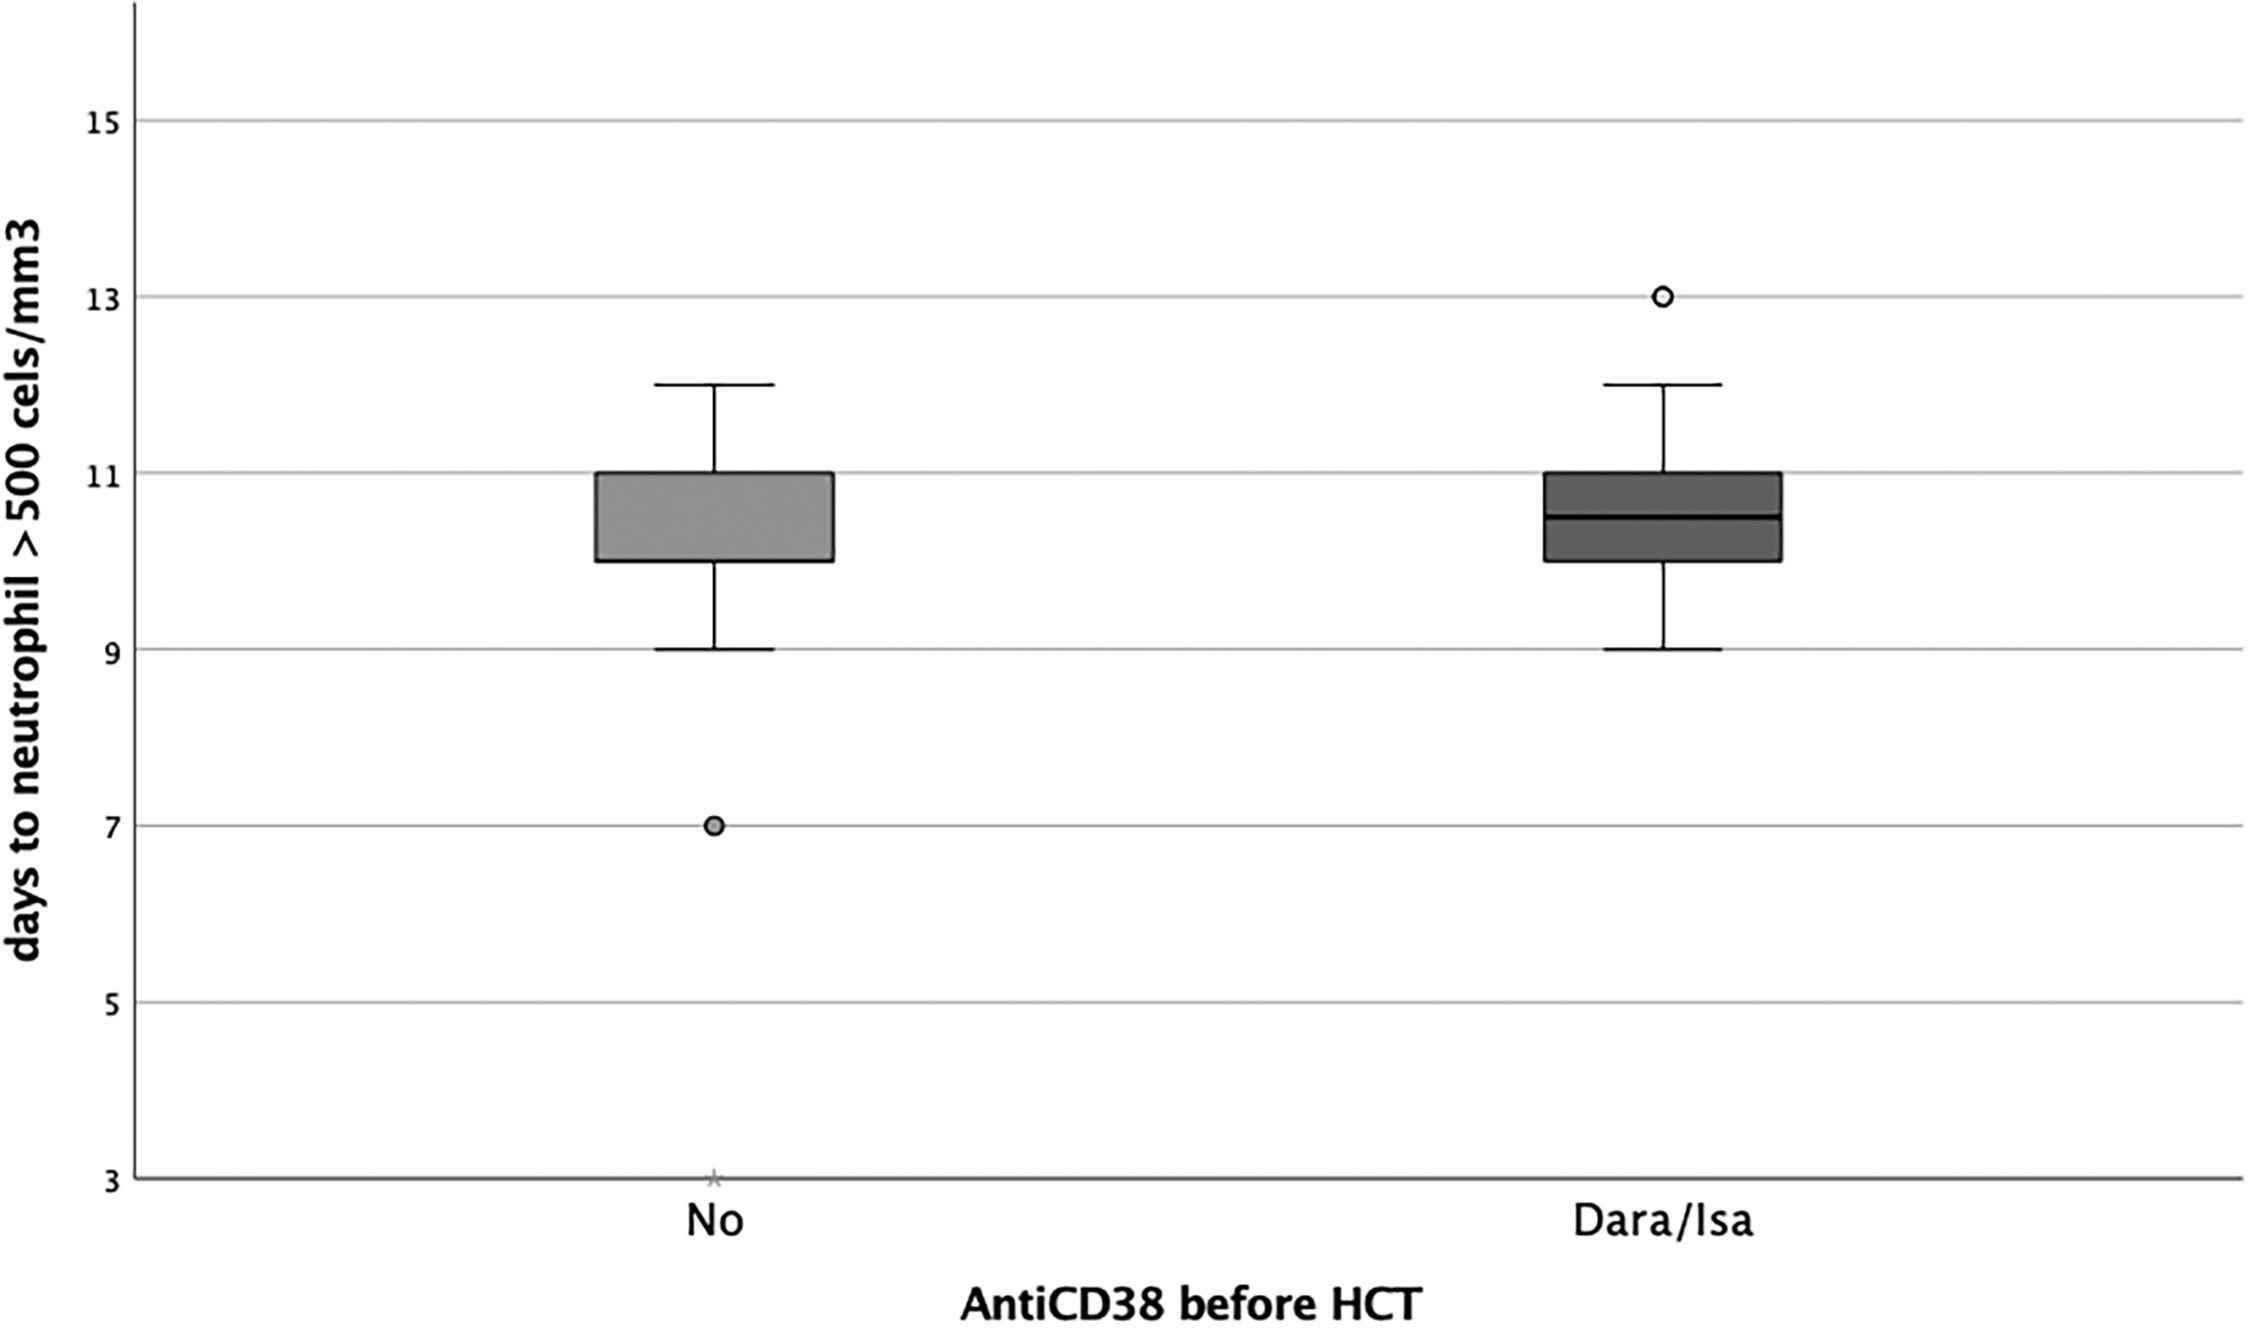
Median time to neutrophil engraftment in the overall cohort was ten days (range: 3–13 days), with no differences observed between anti-CD38–exposed and control patients (10.5 vs. 10 days; p = 0.539) (Figure 2).

As the frequencies of lenalidomide exposition between groups were unbalanced, an additional stratified analysis according to prior lenalidomide exposure (exposed vs. non-exposed) was performed (Supplementary Table S1). In this analysis, no significant differences were observed in CD34+ mobilization, collection yield, plerixafor use, or engraftment outcomes according to lenalidomide exposure status. (Supplementary Table S1).
An exploratory sensitivity analysis was performed by multivariable linear regression models for CD34⁺ PB at Day 4, CD34⁺ yield, and time to engraftment. Prior anti-CD38 exposure was not retained as an independent predictor of any outcome (all p ≥ 0.265).
Transplant-related complicationsFebrile neutropenia occurred in 89% of patients, with no differences between groups (87%vs. 91%; p = 0.751). Bacteremia was documented in 23% of the cohort (24%vs. 22%; p = 1.00). Other cases of febrile neutropenia included 12 with clinical documentation and five that were microbiologically confirmed without bacteremia, all of which occurred in the control group.
Admission to the ICU occurred in 12% of patients, without significant differences between the groups (3 vs. 9; p = 0.134). The incidence of ES was 24%, occurring at the same frequency in both groups (11 vs. 13 patients; p = 1.00).
Hospitalization metrics, including length of stay from Day 0, total hospitalization time, and days from engraftment to discharge, were similar between groups. Only one death occurred in the cohort in a patient without prior anti-CD38 exposure (p = 1.00).
DiscussionThis study assessed whether prior exposure to daratumumab influences hematopoietic stem cell mobilization, CD34⁺ collection, or early post-transplant outcomes in patients undergoing auto-HSCT for multiple myeloma. In this cohort, no significant differences in mobilization efficiency or early transplant-related complications were observed according to prior daratumumab exposure, a finding consistent with the feasibility of auto-HSCT in patients previously treated with these agents. Given the observational design, the limited sample size, and the imbalance in lenalidomide exposure discussed below, these findings should be interpreted as reassuring within the context of this cohort rather than as definitive evidence of equivalence.
Concern that CD38-targeted therapies may interfere with stem cell mobilization stems from their immunologic activity and potential effects on the marrow microenvironment. Previous reports have shown mixed findings: some described reduced CD34⁺ yields or increased plerixafor use after daratumumab exposure, whereas others found no significant impact [9,10,12–16]. In the present cohort, all patients successfully mobilized CD34⁺ cells, no mobilization failures occurred, and PB CD34⁺ counts, pre-apheresis levels, plerixafor use, and final CD34⁺ yields were comparable across both groups. These findings suggest that current mobilization strategies, particularly early or risk-adapted plerixafor, may mitigate any potential negative impact of anti-CD38 therapy.
Prior lenalidomide exposure was significantly more frequent in the control group than in the daratumumab-exposed group (78%vs. 35%; p < 0.001), representing a relevant potential confounder given the well-established association between lenalidomide and impaired stem cell mobilization. Critically, the direction of this imbalance would be expected to bias the comparison against the control group, since a higher proportion of lenalidomide-exposed patients in that arm should, if anything, worsen its mobilization outcomes compared to the daratumumab-exposed group. The fact that no significant between-group differences were observed despite this unfavorable distribution argues against a clinically relevant negative effect of daratumumab exposure on mobilization in this cohort. To further explore this confounder directly, a stratified analysis was performed according to lenalidomide exposure status (exposed: n = 58; non-exposed: n = 42), which is presented in Supplementary Table S1. Within each lenalidomide stratum, CD34⁺ mobilization, plerixafor use, collection yield, and time to engraftment were similar between daratumumab-exposed and unexposed patients, with no statistically significant differences identified. As a complementary sensitivity analysis, an exploratory multivariable assessment was also performed adjusting for prior lenalidomide exposure, age, and sex for the three primary continuous outcomes (CD34⁺ PB at Day 4, CD34⁺ yield, and time to engraftment); the adjusted estimates remained consistent in direction and magnitude with the unadjusted comparisons, although the limited sample size precludes definitive conclusions from this adjusted model. Taken together, these analyses suggest that the lenalidomide imbalance, while a relevant limitation, is unlikely to fully explain the absence of an observed mobilization effect attributable to daratumumab.
Large prospective trials evaluating daratumumab-based induction strategies in transplant-eligible multiple myeloma, including PERSEUS and CASSIOPEIA, demonstrated slightly lower stem cell yields in daratumumab-exposed patients, but without clinically meaningful impairment in auto-HSCT feasibility or hematopoietic recovery [12,4]. The Cassiopeia trial previously demonstrated slightly lower CD34⁺ yields with Dara-VTd versus VTd but no effect on the feasibility or safety of auto-HSCT, confirming preserved engraftment despite anti-CD38 exposure [12].
In PERSEUS, the median CD34+ collection was lower in the D-VRd group (5.5 × 10⁶/kg vs. 7.4 × 10⁶/kg), although transplantation rates and median engraftment time remained similar between the groups [4].
More recently, the DILEMMA study reported increased plerixafor use in daratumumab-exposed patients mobilized with cyclophosphamide [13]. In contrast, the present cohort, mobilized exclusively with G-CSF, showed similar plerixafor requirements (∼25%) in both groups and no mobilization failures, emphasizing the importance of the mobilization strategy when interpreting these differences.
Compared with the findings of Papaiokovou et al. [9], who reported delayed neutrophil recovery and increased early post-transplant complications in patients exposed to daratumumab, the current results showed no negative effect of prior anti-CD38 therapy on engraftment kinetics or early complications. In this cohort, there were similar neutrophil recovery times and preserved graft function regardless of prior anti-CD38 therapy. Early post-transplant complications, including ES, febrile neutropenia, bacteremia, ICU admission, and length of stay, were similarly distributed between groups. Although ES incidence in this population was higher than typically reported, no association with anti-CD38 exposure was observed. Possible explanations include broader clinical recognition and systematic screening for ES, differences in diagnostic criteria, and specific characteristics of heavily pretreated multiple myeloma population at our center. This contrasts with the findings by Minakata et al., who reported a markedly increased ES risk (approximately six-fold) in daratumumab-exposed patients [17].
These findings are consistent with our real-world cohort, in which prior daratumumab exposure was not associated with clinically significant impairment in mobilization, collection yield, or engraftment kinetics. While the study was not prospectively powered, the observed between-group differences were consistently small in magnitude and below established clinical relevance thresholds, suggesting that prior anti-CD38 exposure did not meaningfully impair stem cell mobilization or engraftment in this cohort.
This study has limitations, including sample size, its retrospective nature, single-center design, and potential confounding related to imbalanced prior lenalidomide exposure. A post-hoc power analysis was performed for the three primary continuous outcomes, revealing small effect sizes (Cohen's d: 0.11–0.28) and limited statistical power (8%–28%). While this confirms the study was underpowered to detect subtle differences, all observed between-group differences fell below clinically meaningful thresholds, and no mobilization failures occurred in either group, arguing against a clinically relevant impairment in mobilization. The distribution of missing data did not identify an apparent systematic imbalance between the anti-CD38-exposed and control groups, suggesting that missingness was likely random and related to data availability rather than clinical characteristics or outcomes. Although mobilization protocols were largely standardized, clinician-driven decisions regarding plerixafor use may have introduced variability. These factors may limit generalizability.
In conclusion, in this real-world, single-center cohort, no statistically significant differences in stem cell mobilization, collection yield, engraftment kinetics, or early transplant outcomes were observed between patients with and without prior daratumumab exposure. Given the observational design, the limited sample size, and the residual confounding by lenalidomide exposure discussed above, these findings should not be interpreted as proof of clinical equivalence, but rather as reassuring evidence, within the limits of this cohort, that auto-HSCT remains feasible following daratumumab-based induction. As anti-CD38-containing regimens continue to expand in frontline therapy, prospective, adequately powered, multicenter studies are warranted to confirm these observations.
Ethics approvalApproved by the Institutional Review Board of Hospital Nove de Julho, (approval number: CAAE 54941216.0.3001.5455). The requirement for informed consent was waived due to the retrospective design.
Declaration of AI-assisted technologies in the manuscript preparation processDuring the preparation of this manuscript, the authors used Grammarly, ChatGPT, and Claude (Anthropic) to assist with language editing and revision. These tools were used solely to improve clarity, grammar, and readability of the text; no AI tool was used to generate scientific content, data, analyses, or conclusions. After using these tools, the authors critically reviewed and edited the content as needed and take full responsibility for the accuracy, integrity, and originality of the published work.
Data availabilityThe data that support the findings of this study are available from the corresponding author upon reasonable request.
None of the authors has any conflicts of interest (direct or indirect) concerning the contents of the manuscript.
MG received grants from Fundacao de Amparo a Pesquisa do Rio de Janeiro (FAPERJ); AM received grants from CNPq and Fundacao de Amparo a Pesquisa do Rio de Janeiro (FAPERJ).






